How Many People Get Yellow Eyelid Plaques, Who Is Most Likely To, Why Women And Middle Age Lead The Numbers, And What It Means If You Have Them
Xanthelasma is fairly common: it affects about 1.1% of women and 0.3% of men, most often between the ages of 35 and 55. It’s the type of cholesterol deposit on the eyelids that doctors see most, and it’s harmless in itself, but because about half of people with it have a lipid disorder, being common doesn’t mean it’s nothing to check.
Yes, xanthelasma is fairly common. About 1.1% of women and 0.3% of men have it, so it’s several times more common in women. It usually appears between 35 and 55, though it’s seen from about 20 to 70. About half of people with it have a lipid disorder, so a doctor’s blood test is worthwhile.
Key Takeaways
- About 1.1% of women and 0.3% of men have xanthelasma.
- It’s most common between 35 and 55, and rare in children.
- About half of people with it have a lipid disorder.
- Inherited high cholesterol, found in about 1 in 250 to 500 people, raises the odds.
- It’s linked with higher heart risk, even with normal cholesterol.
- It rarely fades by itself, but it can be removed.
On This Page 16 sections
Is Xanthelasma Common?
Yes, it’s fairly common. It isn’t rare enough to be unusual, but it isn’t something most people get either: roughly 1 in 90 women and 1 in 330 men have it.
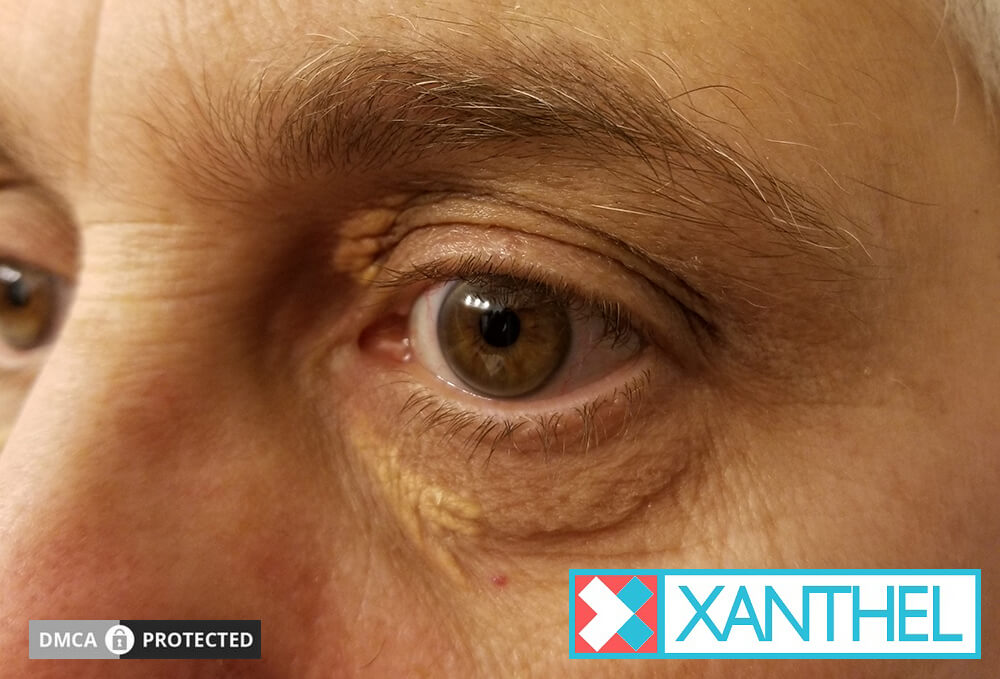
Xanthelasma palpebrarum is a soft, yellow, flat or slightly raised plaque on the eyelids, usually near the inner corners. It’s made of foam cells, immune cells loaded with cholesterol, that collect in the deeper layer of the eyelid skin.[1] Of all the fatty deposits that can form in the skin, these yellow spots on the eyelids are the ones people notice and ask about most.
So if you’ve spotted them, you’re far from alone, and doctors will recognize them straight away. Our guides to xanthelasma and what xanthelasma is explain the condition in full, and our page on how common xanthelasma is looks at the numbers from another angle.

How Common Is Xanthelasma, In Numbers?
About 1.1% of women and 0.3% of men, according to StatPearls. In a group of 1,000 women, about 11 would have it; in 1,000 men, about 3.
Women
- About 1.1% have xanthelasma
- Roughly 11 in every 1,000
- The majority of people seen with it
Men
- About 0.3% have xanthelasma
- Roughly 3 in every 1,000
- Less often affected, but not immune
Those are the figures in StatPearls, the National Library of Medicine’s clinical reference.[1] Studies of people seen in clinics show the same pattern: in one study of 42 people with xanthelasma, 85.7% were women and the average age was about 47.[2] Estimates vary between studies and populations, so take any single number as a guide rather than an exact count.

Why Do Estimates Of How Common Xanthelasma Is Vary?
Because studies count different groups of people in different ways. Clinic studies only see people who came in for help, population surveys depend on who takes part, and the share of older people, women and people with high cholesterol changes from place to place.
A figure from a dermatology clinic will look very different from one taken from a general health survey, simply because people with eyelid marks are the ones who go to dermatologists. That’s why clinic studies tend to show a strong female majority and an average age in the late forties, while population figures are lower overall. Small, flat plaques are also easy to miss or mistake for something else, so some cases are never counted at all.
The practical point doesn’t change with the exact number: if you have xanthelasma, you’re in good company, and the right next step is a routine blood test rather than worrying about where you sit in the statistics.

At What Age Is Xanthelasma Most Common?
Between 35 and 55. It’s been seen from about age 20 to 70, but middle age is when most people first notice it.
StatPearls gives the age range as roughly 20 to 70, with a peak between 35 and 55.[1] That fits with how it forms: small eyelid blood vessels become leakier with age, and the constant squeeze of blinking may help cholesterol escape into the skin, where it builds up slowly over years.[1]
Plaques usually start small and flat, often on the upper lid near the nose, then may slowly widen or appear on other lids. Our pages on how xanthelasma starts and where xanthelasma appears describe the early signs.

Why Is Xanthelasma More Common In Women?
Nobody knows for certain. Hormonal factors are a likely part of it, since estrogen medicines are a recognized secondary cause and many women with xanthelasma have normal cholesterol.
StatPearls lists estrogens and retinoids among the medicines that can contribute to xanthelasma.[1] In the study where 85.7% of patients were women, more than half had normal total cholesterol, and the authors suggested that local, hormonal or immune-cell factors might explain why plaques form even without raised cholesterol.[2]
Women may also notice and seek help for eyelid changes more often, which can tilt clinic figures. Whatever the reason, the advice is the same for everyone: get the blood test. Our guide to the causes of xanthelasma goes into the theories.

Can Young People Get Xanthelasma?

Yes, though it’s uncommon before 30 and rare in children. When it appears young, an inherited lipid disorder such as familial hypercholesterolemia is much more likely and should be checked.
StatPearls advises considering an inherited dyslipidemia whenever xanthelasma appears at a young age.[1] Familial hypercholesterolemia affects about 1 in 250 to 1 in 500 people, passes to each child with a 50% chance, and can cause xanthelasma as well as firm tendon lumps on the Achilles, elbows, hands, knees or feet.[4] Without management, about 50% of men with it have a coronary event by 50, which is why early diagnosis matters so much.[4]
Our pages on whether xanthelasma is genetic and on tendon xanthomas explain the family link.
Who Is Most Likely To Get Xanthelasma?
Middle-aged women, people with raised LDL or triglycerides or low HDL, people with a family history of high cholesterol, and those with diabetes, an underactive thyroid or certain liver or kidney conditions.
StatPearls splits the causes into primary lipid disorders and secondary causes.[1]
Primary Lipid Disorders
- High LDL cholesterol (type IIa)
- High cholesterol and triglycerides (type IIb)
- High triglycerides (type IV)
- Low HDL cholesterol
- Inherited high cholesterol
Secondary Causes
- Diabetes
- Underactive thyroid
- Nephrotic syndrome (a kidney condition)
- Primary biliary cholangitis (a liver condition)
- Retinoid or estrogen medicines
Smoking, weight and diet influence cholesterol, so they play a part through those numbers. Our page on whether xanthelasma indicates raised cholesterol explains the link.

Does Having Xanthelasma Mean Your Cholesterol Is High?
Not always. About half of people with xanthelasma have a lipid disorder, and about half don’t. Even with normal total cholesterol, HDL is often low.
StatPearls puts the share with a primary or secondary lipid disorder at about 50%.[1] In the clinic study, 45.2% had high cholesterol and 54.8% normal, but median HDL was 36.2 mg/dL compared with 50.5 mg/dL in people without xanthelasma, and 26.2% had familial hyperlipidemia.[2] A 2020 review of 15 studies with 854 patients found higher total cholesterol, LDL and apolipoprotein B, and lower apolipoprotein A1, in people with xanthelasma.[3]
So the only way to know is a blood test: a fasting lipid profile, liver panel, thyroid tests and fasting glucose.[1]

If Xanthelasma Is Common, Why Bother Getting It Checked?
Because common doesn’t mean meaningless. Xanthelasma has been linked with a higher risk of heart attack and heart disease, even after allowing for cholesterol, so it’s a useful prompt to look after your heart.
In a Copenhagen study of almost 13,000 people followed for decades, those with xanthelasma had a higher risk of heart attack and heart disease, independent of cholesterol.[5] The 2020 review also found thicker carotid artery walls and a higher risk of atherosclerosis in people with xanthelasma.[3]
This isn’t a reason to worry; it’s a reason to get a simple check and act on it. Our guide to whether xanthelasma is dangerous explains the risk in plain terms.

How Does Xanthelasma Compare With Other Eyelid Bumps?
Xanthelasma is the yellow, soft, flat-to-raised one. Milia are tiny white beads, syringomas are small skin-colored bumps, and other xanthomas usually appear elsewhere on the body.
- Xanthelasma. Soft yellow plaques on the eyelids, often near the inner corners.
- Milia. Tiny, hard, white, pearl-like spots.
- Syringomas. Small, firm, skin-colored or yellowish bumps, often in clusters under the eyes.
- Tendon xanthomas. Firm lumps over tendons, a sign of inherited high cholesterol.[4]
- Eruptive xanthomas. Crops of small yellow-red bumps, usually on the buttocks, arms or legs, with very high triglycerides.
A doctor can tell them apart, and a firm, bleeding or fast-changing mark should always be checked. Our guides to what can look like xanthelasma, xanthomas and eruptive xanthoma go further.

How Common Is Xanthelasma: The Figures At A Glance
| Question | Answer | Source |
|---|---|---|
| How many women have it? | About 1.1% | StatPearls |
| How many men have it? | About 0.3% | StatPearls |
| Usual age range | About 20 to 70, most often 35 to 55 | StatPearls |
| Share with a lipid disorder | About 50% | StatPearls |
| Share of patients who are women (one clinic study) | 85.7% | Kavoussi 2016 |
| Inherited high cholesterol in the population | About 1 in 250 to 1 in 500 | GeneReviews |
| Chance it comes back after removal | Generally under 50% | StatPearls |
Is It Normal To Get Xanthelasma?
It’s common and harmless in itself, so there’s nothing strange about having it. But it isn’t a normal part of ageing that everyone gets, which is why a doctor’s check is sensible.
Xanthelasma doesn’t hurt, itch or affect your eyesight, and it isn’t contagious or cancerous. Many people with it are otherwise completely healthy. Think of it as a harmless mark that’s worth one routine appointment: confirm what it is, get your blood tested, and then decide what you’d like to do about the look of it. Our guide to what xanthelasma looks like helps you recognize it.

Does Common Xanthelasma Go Away By Itself?

Rarely. Once plaques form they tend to stay the same or slowly grow, and lowering cholesterol doesn’t usually make them shrink. Removing them is what clears them.
The fat is held inside foam cells woven into the skin, so it doesn’t drain away. Plaques can widen, thicken or appear on other lids over time, and larger, deeper ones are harder to remove and more likely to come back.[1] Our page on whether xanthelasma can go away on its own covers this honestly.

What Should You Do If You Have Xanthelasma?
See your doctor for a blood test, manage any cause they find, then choose whether to leave the plaques, cover them with makeup or remove them at home or at a clinic.
Clinic removal includes laser, surgery and other methods; in a 2023 review, CO2 laser gave over 75% improvement in over 90% of patients, with surgery kept for larger, deeper plaques.[6] Small to medium plaques can also be removed at home with a cream made for xanthelasma removal, with about one to two weeks of healing. If you’d rather cover them for now, our guide to hiding xanthelasma with makeup shows how.
Our step-by-step plan on what to do about xanthelasma, and our guides on how to remove xanthelasma and xanthelasma home removal, help you choose.

If you’ve had your check and would like the plaques gone, this is the cream we make for xanthelasma removal at home.
What’s The Bottom Line On Whether Xanthelasma Is Common?
Xanthelasma is fairly common, affecting about 1.1% of women and 0.3% of men, mostly between 35 and 55. It’s harmless in itself, but about half of people with it have a lipid disorder and it’s linked with higher heart risk, so a blood test is worthwhile. It rarely fades by itself, and it can be covered or removed.
Xanthel® is a cosmetic cream made for xanthelasma removal at home, sold by Xanthelasma.com. You’ll find it in the section above and at the foot of this page, or read more about Xanthel® xanthelasma removal cream. For everything else, browse all our xanthelasma guides.
Common Questions About How Common Xanthelasma Is
How Common Is Xanthelasma?
It affects about 1.1% of women and 0.3% of men, or roughly 11 in 1,000 women and 3 in 1,000 men.
Who Is Most Likely To Get Xanthelasma?
Middle-aged women, and people with high LDL or triglycerides, low HDL, inherited high cholesterol, diabetes, an underactive thyroid or certain liver or kidney conditions.
Is It Normal To Get Xanthelasma?
It’s common and harmless in itself, but it isn’t something everyone gets with age, so a doctor’s check is sensible.
Can Young People Get Xanthelasma?
Yes, though it’s uncommon before 30; in young people an inherited lipid disorder is more likely and should be tested for.
Is Xanthelasma More Common In Women?
Yes, about 1.1% of women have it compared with 0.3% of men, possibly partly because of hormonal factors.
At What Age Does Xanthelasma Usually Appear?
Most often between 35 and 55, though it’s seen from about 20 to 70.
Does Having Xanthelasma Mean My Cholesterol Is High?

Not always; about half of people with it have a lipid disorder, and even with normal total cholesterol HDL is often low, so a blood test is the only way to know.
Does Xanthelasma Go Away By Itself?
Rarely; plaques tend to stay or slowly grow, but they can be removed at home or at a clinic.
Sources
- Blair K. Xanthelasma Palpebrarum. StatPearls, National Library of Medicine (NCBI Bookshelf), updated 2026.
- Kavoussi H, Ebrahimi A, Rezaei M, Ramezani M, Najafi B, Kavoussi R. Serum lipid profile and clinical characteristics of patients with xanthelasma palpebrarum. Anais Brasileiros de Dermatologia, 2016;91(4):468-471.
- Chang HC, Sung CW, Lin MH. Serum lipids and risk of atherosclerosis in xanthelasma palpebrarum: a systematic review and meta-analysis. Journal of the American Academy of Dermatology, 2020;82(3):596-605.
- Ison HE, Clarke SL, Knowles JW. Familial Hypercholesterolemia. GeneReviews, National Library of Medicine (NCBI Bookshelf), revised 2025.
- Christoffersen M, Frikke-Schmidt R, Schnohr P, Jensen GB, Nordestgaard BG, Tybjaerg-Hansen A. Xanthelasmata, arcus corneae, and ischaemic vascular disease and death in general population: prospective cohort study. BMJ, 2011.
- Malekzadeh H, Ormseth B, Janis JE. A Practical Review of the Management of Xanthelasma Palpebrarum. Plastic and Reconstructive Surgery Global Open, 2023;11(5):e4982.