The Medical Name Explained: What Doctors See, What It Signals, And Every Removal Option Compared
Xanthelasma palpebrarum is the full medical name for the soft yellow plaques that form on the eyelids, made of fat-filled immune cells in the skin. It’s the most common type of xanthoma, harmless in itself, and linked to a blood fat disorder in about half of people. Here’s the clinical picture of xanthelasma palpebrarum, from what it looks like under the microscope to every way of removing it.
Xanthelasma palpebrarum means “yellow plaques of the eyelids”. It’s a buildup of fat-filled foam cells in the eyelid skin, seen in about 1.1% of women and 0.3% of men. About half have a lipid disorder, so doctors check blood fats. It rarely fades, but laser, surgery, peels, freezing or at-home removal can clear it.
Key Takeaways
- Xanthelasma palpebrarum is the medical name for yellow plaques on the eyelids.
- The plaques are made of fat-filled immune cells called foam cells.
- About half of people with it have a primary or secondary lipid disorder.
- It’s linked with higher LDL cholesterol and a higher risk of heart disease.
- Removal methods include laser, surgery, chemical peels, freezing and at-home creams.
- Deeper plaques are more likely to come back after removal.
On This Page 14 sections
What Does Xanthelasma Palpebrarum Mean?
It means “yellow plaque of the eyelids”. Xanthelasma comes from the Greek words for yellow (xanthos) and a beaten metal plate (elasma), and palpebrarum is Latin for “of the eyelids”. It’s the same condition most people simply call xanthelasma.
Doctors add “palpebrarum” to be precise, because the word xanthelasma on its own is occasionally used for yellow fatty patches elsewhere, such as in the stomach lining. In everyday use, though, xanthelasma, xanthelasma palpebrarum and “XP” in medical papers all refer to the same soft yellow plaques on the eyelids. You’ll also see them described as cholesterol deposits on the eyelids or fatty deposits around the eyes.
Xanthelasma palpebrarum belongs to a wider family called xanthomas, which are fat-filled deposits in the skin or tendons, and it’s the most common member of that family.[1] Our guides to what xanthelasma palpebrarum is, the meaning of xanthelasma in medical terms and how to pronounce xanthelasma (zan-thuh-LAZ-muh) cover the name in more detail, and xanthomas covers the wider family.

Who Gets Xanthelasma Palpebrarum?
It affects about 1.1% of women and 0.3% of men, so it’s close to four times more common in women. It usually appears in middle age, most often between about 35 and 55, though it can start from the teens to the seventies.
Clinical reviews put the prevalence at around 1.1% in women and 0.3% in men.[1][2] It’s seen from about age 20 to 70, most often between 35 and 55,[1] and another review reports onset as early as 15 and as late as 73, with a peak between 30 and 50.[2]
When xanthelasma palpebrarum appears in younger people, doctors pay closer attention, because an inherited lipid disorder is more likely to be behind it.[1] Our guide on how common xanthelasma is looks at the numbers in more depth, and is xanthelasma genetic covers the family link.

How Do You Recognize Xanthelasma Palpebrarum?
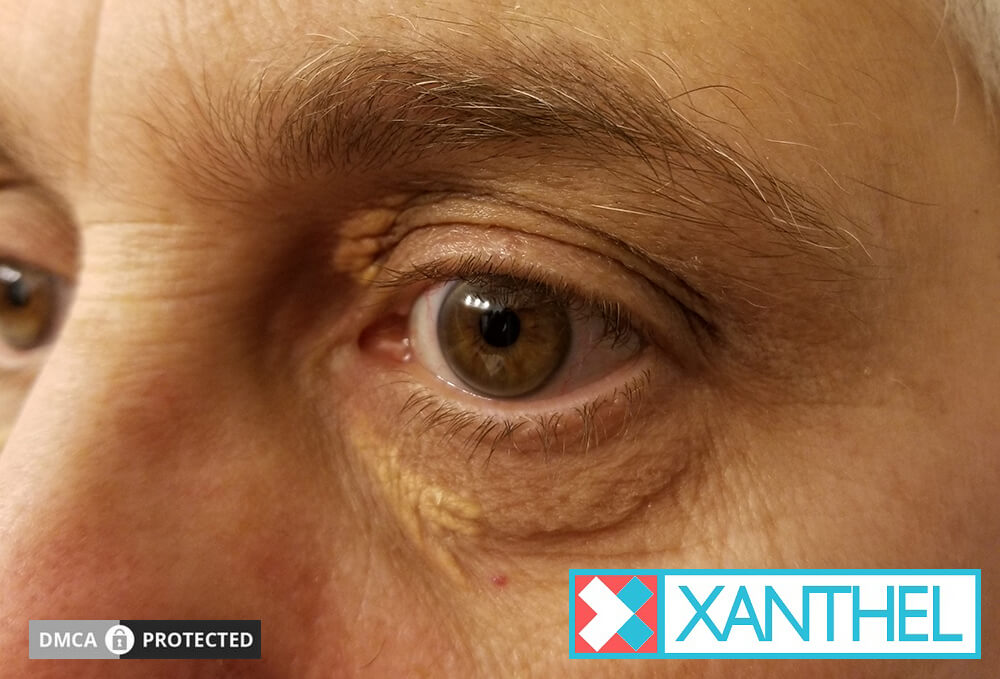
Look for soft, yellow to yellow-orange plaques with fairly clear edges, usually near the inner corners of the upper eyelids and on both sides. They’re painless, don’t itch and don’t affect your vision.
The classic features are:
- Color. Yellow to yellow-orange, from stored fat showing through thin skin.
- Location. Most often the inner corner of the upper lid, close to the nose.[2]
- Symmetry. Usually on both eyes in a similar position.[2]
- Texture. Flat and soft, or firmer and nodular in longer-standing plaques.[2]
- Comfort. No pain, itching or effect on how the eyelid works; reviews describe it as a cosmetic condition that never limits function.[2]
Plaques can stay small for years or slowly grow and merge. Our guides on xanthelasma around the eyes and whether xanthelasma can be flat show the range of appearances, and what can look like xanthelasma covers lookalikes such as milia and syringomas.

What Is Xanthelasma Palpebrarum Under The Microscope?
Under the microscope, xanthelasma palpebrarum is a cluster of foam cells: immune cells called macrophages that have filled with fat. They sit in the deeper layer of the skin, around small blood vessels, with some inflammation.
The process starts with fat leaking from the tiny blood vessels of the eyelid. Researchers think blinking squeezes these capillaries and that they become leakier with age, letting fat-carrying particles escape into the skin. Macrophages swallow the fat, and once overloaded they become foam cells that gather in the reticular dermis, the deeper part of the skin, around the vessels.[1]
This explains three things people often ask about. The plaques are yellow because you’re seeing stored fat through very thin skin. They don’t drain away, because the fat is locked inside living cells. And they can’t be squeezed out, because there’s no pocket of loose fluid to release. Our guide to how xanthelasma forms walks through the process.

How Do Doctors Grade Xanthelasma Palpebrarum?
A common system grades it from I to IV by how much of the eyelids it covers, from the upper lids only to widespread plaques on all four lids. Doctors also note how high and how firm the plaques are.
The grades are:[2]
- Grade I. Upper eyelids only.
- Grade II. Extending into the inner corner of the eye.
- Grade III. The inner side of both upper and lower eyelids.
- Grade IV. Widespread, on the inner and outer sides of upper and lower lids.

Alongside the grade, doctors record the height of the plaque, whether it’s soft or hard, and how long it’s been there, because these decide which removal methods suit it.[2] A soft, flat, grade I plaque is the simplest to deal with; a hard, raised grade IV pattern is the most demanding.

What Can Xanthelasma Palpebrarum Signal About Your Health?
The plaques are harmless, but they can be a visible clue to raised blood fats. About half of people with xanthelasma palpebrarum have a lipid disorder, and studies link it with higher LDL cholesterol, thicker artery walls and a higher risk of heart disease.
About 50% of people with xanthelasma palpebrarum have a primary or secondary lipid disorder.[1] When researchers pooled 15 case-control studies covering 854 patients, those with xanthelasma had higher total cholesterol, LDL and apolipoprotein B, lower apolipoprotein A1, and thicker carotid artery walls, a sign of early hardening of the arteries.[3]
The heart link holds even for people with normal cholesterol. A Danish study that followed almost 13,000 people for decades found that xanthelasma was linked with a higher risk of heart attack and heart disease, independent of cholesterol levels.[4] That’s a pattern across large groups, not a forecast for any one person, but it’s why a check-up is worthwhile. Our guide on whether xanthelasma is dangerous puts the risk in proportion.

Which Conditions Are Linked With Xanthelasma Palpebrarum?
Primary lipid disorders, such as raised LDL, mixed high cholesterol and triglycerides, or low HDL, are the most common. Secondary causes include diabetes, an underactive thyroid, primary biliary cholangitis, nephrotic syndrome and taking retinoid or estrogen medicines.
Doctors group the associated conditions into two kinds:[1]
Primary Lipid Disorders
- Raised LDL cholesterol (type IIa)
- Raised cholesterol and triglycerides (types IIb and IV)
- Low HDL cholesterol
- Inherited disorders, especially in younger people
Secondary Causes
- Diabetes
- Underactive thyroid
- Primary biliary cholangitis and nephrotic syndrome
- Taking retinoid or estrogen medicines
Sarcoidosis has also been reported alongside it.[1] The other half of people have normal blood tests, and local eyelid factors, such as leakier vessels with age, are thought to explain their plaques. Our guide to the causes of xanthelasma covers each cause in depth.

How Is Xanthelasma Palpebrarum Diagnosed And Checked?
A doctor usually recognizes it just by looking. The important part is the follow-up: blood tests for cholesterol, liver, thyroid and blood sugar to look for anything behind it. A biopsy is only needed if the diagnosis is uncertain.
The standard workup includes:[1]
- A look at the plaques. Their color, position and symmetry are usually enough to confirm xanthelasma.
- Fasting lipid profile. Total cholesterol, LDL, HDL and triglycerides.
- Liver panel. To look for liver conditions such as primary biliary cholangitis.
- Thyroid function tests. To rule out an underactive thyroid.
- Fasting glucose, and HbA1c in people with diabetes. To check blood sugar control.
- A skin biopsy, if unsure. Rarely needed, but it shows the foam cells clearly.
Your family doctor is the right starting point and can refer you on if needed; our guide on which doctor to see about xanthelasma explains who does what.

How Is Xanthelasma Palpebrarum Removed?
It can be removed with laser, surgical excision, chemical peels, freezing, radiofrequency or an at-home cream. The right choice depends on the plaque’s size, depth and position, and on how you feel about clinic procedures near your eyes.
Xanthelasma palpebrarum rarely goes away by itself, and managing cholesterol protects your health more than it shrinks existing plaques. Removal is a separate step. Clinical reviews suggest matching the method to the plaque: soft, superficial plaques under 5 mm high that have been present under a year suit laser, radiofrequency, chemical peels or freezing, while deeper, harder or longer-standing plaques, especially those reaching the eyelid muscle, usually suit surgery.[2]
The evidence for laser is strong: a review of 49 studies found CO2 laser gave more than 75% improvement in over 90% of patients, and Er:YAG laser more than 80% improvement, with skin color changes the most common complication. CO2 laser also outperformed 30% to 50% acid peels.[5] Surgery is used for larger, deeper plaques,[5] but it can cause the lower lid to turn outward or the lid to pull back, and freezing or chemical methods can scar or discolor the skin.[1] The table below sums up the options, and our guides to the removal of xanthelasma and how to remove xanthelasma palpebrarum go into each one.
Many people prefer to avoid a clinic altogether and deal with their plaques at home. If you’ve had your blood fats checked and want to do that, this is the cream we make for xanthelasma palpebrarum.

Xanthelasma Palpebrarum Removal Methods Compared
| Method | Best Suited To | What The Evidence Shows | Main Downsides |
|---|---|---|---|
| Xanthel® at home | People who’d rather avoid a clinic | Cosmetic cream applied only to the plaque; results vary | About one to two weeks of healing; cause still needs checking |
| CO2 laser | Superficial plaques | Over 75% improvement in over 90% of patients | Skin color changes; clinic visits |
| Er:YAG laser | Superficial plaques | Over 80% improvement | Skin color changes; clinic visits |
| Surgical excision | Large, deep or hard plaques | Removes deep plaques in one go | Scarring; lower lid turning out or pulling back |
| Chemical peel (TCA) | Flat and smaller plaques | Strength matched to plaque thickness | Scarring and color change; outperformed by CO2 laser |
| Freezing (cryotherapy) | Superficial plaques | Cleared nearly all in one 100-patient series | Lighter patches of skin; 26 of 100 came back |
Do Home Remedies Work On Xanthelasma Palpebrarum?

There’s no good evidence that they do, and some are harmful. Garlic has caused second-degree burns and scarring on the skin, and we haven’t found any published evidence that castor oil, almond oil or other oils remove xanthelasma.
Because the fat sits inside living cells deep in the skin, rubbing something on the surface can’t dissolve it. Some remedies do damage instead. A systematic review of 39 reported garlic burn cases found mostly second-degree burns, with some scarring, particularly on the face.[6] On eyelid skin, the thinnest on the body, that’s a real risk.
Oils such as castor oil and almond oil are popular online, but we haven’t found any published evidence that they remove xanthelasma palpebrarum. Squeezing or picking doesn’t work either, since there’s no loose fat to release. A healthy diet and staying active are worth it for your heart and may help limit new plaques, but they aren’t a removal method. Our guide on how to get rid of xanthelasma palpebrarum covers the options that do work, and xanthelasma cream covers the at-home route.

Does Xanthelasma Palpebrarum Come Back After Removal?
It can. Recurrence is generally under 50%, but it’s higher for deeper plaques, after repeated procedures and when all four eyelids are involved. Managing any lipid disorder gives you the best chance of fewer new plaques.
Recurrence is generally reported at under 50%, and deeper plaques come back more often.[1] One widely quoted surgical report found recurrence of 40% after a first excision, 60% after a second, and 80% when all four eyelids were affected, with about a quarter of recurrences in the first year.[2] In the 100-patient freezing series, 26 plaques came back.[2]
New plaques form because the cause is often ongoing. Keeping cholesterol, thyroid and blood sugar in check, and dealing with plaques while they’re still small and flat, both help. Our guide on whether xanthelasma comes back covers recurrence in full.

What’s The Bottom Line On Xanthelasma Palpebrarum?
Xanthelasma palpebrarum is the medical name for harmless yellow plaques of fat-filled cells on the eyelids. About half of people with it have a lipid disorder, so get your blood fats checked, then choose the removal method that suits your plaques.
Laser and surgery work well in the right hands, and many people prefer to deal with their plaques at home. Xanthel® is a cosmetic cream made for xanthelasma removal at home, sold by Xanthelasma.com. You’ll find it at the foot of this page, or read more about Xanthel® xanthelasma removal cream, see our main xanthelasma guide and browse all our xanthelasma guides.
Common Questions About Xanthelasma Palpebrarum
Is Xanthelasma Palpebrarum The Same As Xanthelasma?
Yes. Xanthelasma palpebrarum is the full medical name, meaning yellow plaques of the eyelids, and it’s the same condition most people simply call xanthelasma.
Is Xanthelasma Palpebrarum Dangerous?
No, the plaques themselves are harmless. About half of people with it have a lipid disorder, though, and it’s linked with a higher risk of heart disease, so a check-up is worthwhile.
Does Xanthelasma Palpebrarum Mean High Cholesterol?
Not always. About half of people with it have a lipid disorder and about half have normal blood fats, so a fasting lipid profile is the way to find out.
What Is Xanthelasma Palpebrarum Made Of?
It’s made of foam cells, which are immune cells called macrophages that have filled with fat, sitting in the deeper layer of the eyelid skin around small blood vessels.
Does Xanthelasma Palpebrarum Affect Eyesight?
No. It sits in the eyelid skin, not the eye, and it doesn’t affect vision or how the eyelids open and close.
What Is The Best Way To Remove Xanthelasma Palpebrarum?
It depends on the plaque. Laser suits superficial plaques, surgery suits large or deep ones, and many people prefer an at-home cream to avoid clinic procedures near the eyes.
Can Xanthelasma Palpebrarum Go Away On Its Own?
Rarely. The fat is locked inside cells in the skin, so plaques usually stay or slowly grow unless they’re removed.
Can I Remove Xanthelasma Palpebrarum At Home?
Yes, many people do. Once your doctor has checked your blood fats, an at-home cream such as Xanthel®, applied only to the plaque, is one way to deal with it.
Sources
- Blair K. Xanthelasma Palpebrarum. StatPearls, National Library of Medicine (NCBI Bookshelf), updated 2026.
- Nair PA, Singhal R. Xanthelasma palpebrarum: a brief review. Clinical, Cosmetic and Investigational Dermatology, 2017;11:1-5.
- Chang HC, Sung CW, Lin MH. Serum lipids and risk of atherosclerosis in xanthelasma palpebrarum: a systematic review and meta-analysis. Journal of the American Academy of Dermatology, 2020;82(3):596-605.
- Christoffersen M, Frikke-Schmidt R, Schnohr P, Jensen GB, Nordestgaard BG, Tybjaerg-Hansen A. Xanthelasmata, arcus corneae, and ischaemic vascular disease and death in general population: prospective cohort study. BMJ, 2011.
- Malekzadeh H, Ormseth B, Janis JE. A Practical Review of the Management of Xanthelasma Palpebrarum. Plastic and Reconstructive Surgery Global Open, 2023;11(5):e4982.
- Hitl M, Kladar N, Gavaric N, Srdenovic Conic B, Bozin B. Garlic burn injuries: a systematic review of reported cases. American Journal of Emergency Medicine, 2021.